Connected Health and Wearables · Study deck
Medication IoT: Integration, Evidence, and Safety
A dispenser and sensor can record an event, yet the clinic still cannot act until the event reaches the right patient record with its limits intact.
Ada is your guide for this deck.
After studying this chapter
Learning objectives
You will be able to:
- map medication evidence into an EHR care workflow
- evaluate privacy, accuracy, and compliance costs
- test ROI and regulatory assumptions with a medication safety gate
- Explain: The Integration Gap: Despite the promise of consumer health wearables and IoT medical devices, lack of Electronic Health Record (EHR) integration remains the primary barrier to clinical adoption.
Major section
EHR Integration Barrier
The Integration Gap: Despite the promise of consumer health wearables and IoT medical devices, lack of Electronic Health Record (EHR) integration remains the primary barrier to clinical adoption.
- A device that doesn't flow data into the patient's medical record is, from a clinical workflow perspective, invisible.
- The FHIR Standard: A Path Forward.
Major section
EHR Integration Barrier (continued)
"Sometimes, a dumb gadget can be as useful as a smart one if it could integrate seamlessly with the EHR.".
- Legacy systems: Most EHRs (Epic, Cerner, Meditech) are 20+ year old architectures.
- The question isn't "what can we measure?" but "what can we get into the clinical record?".
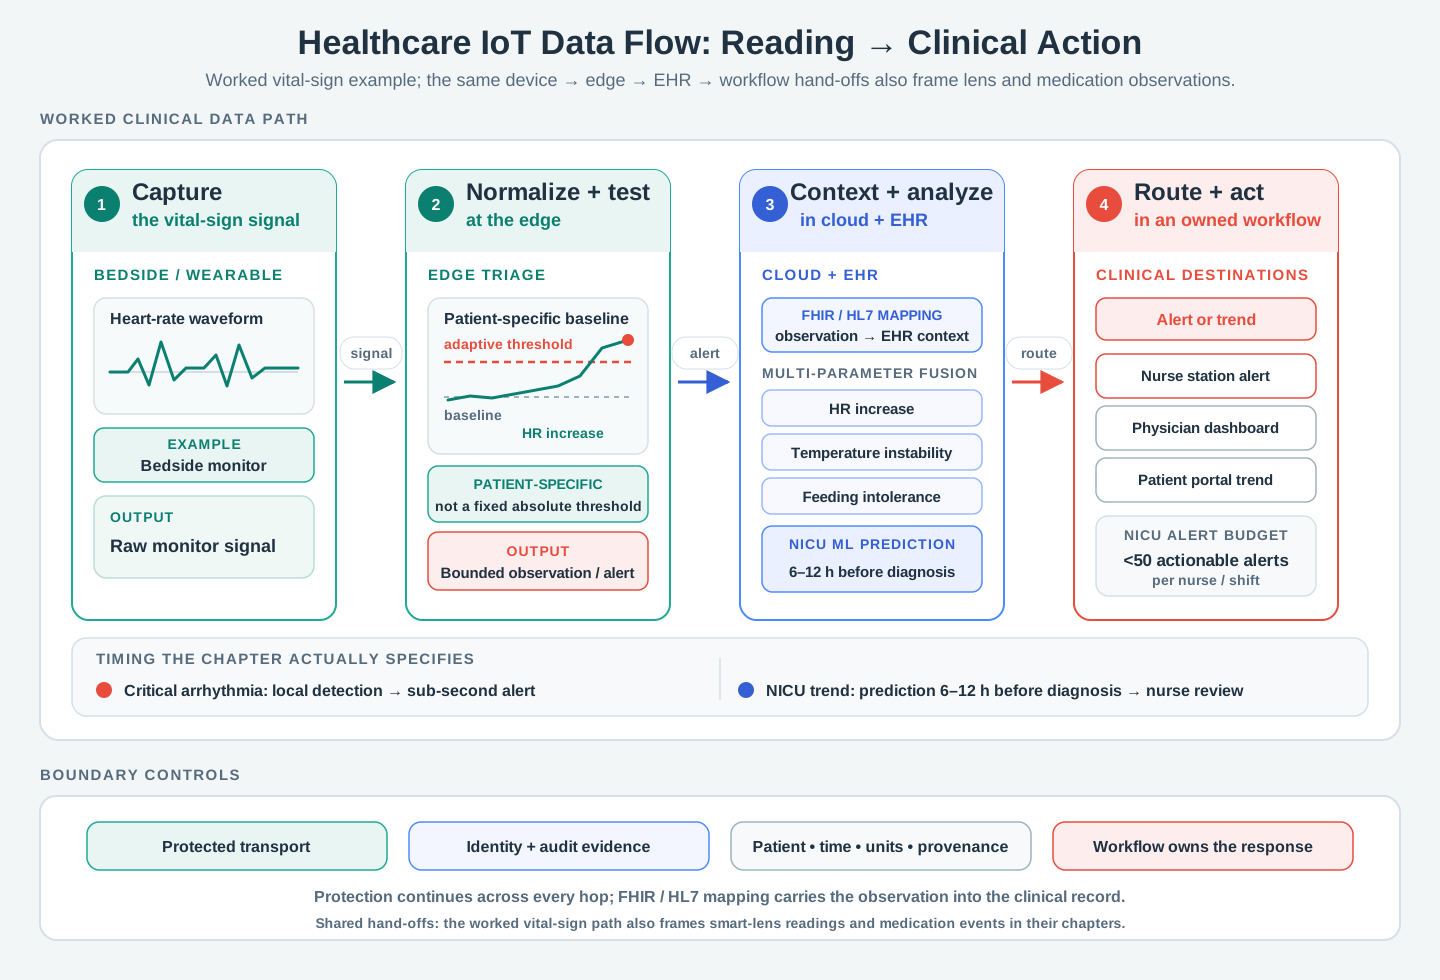
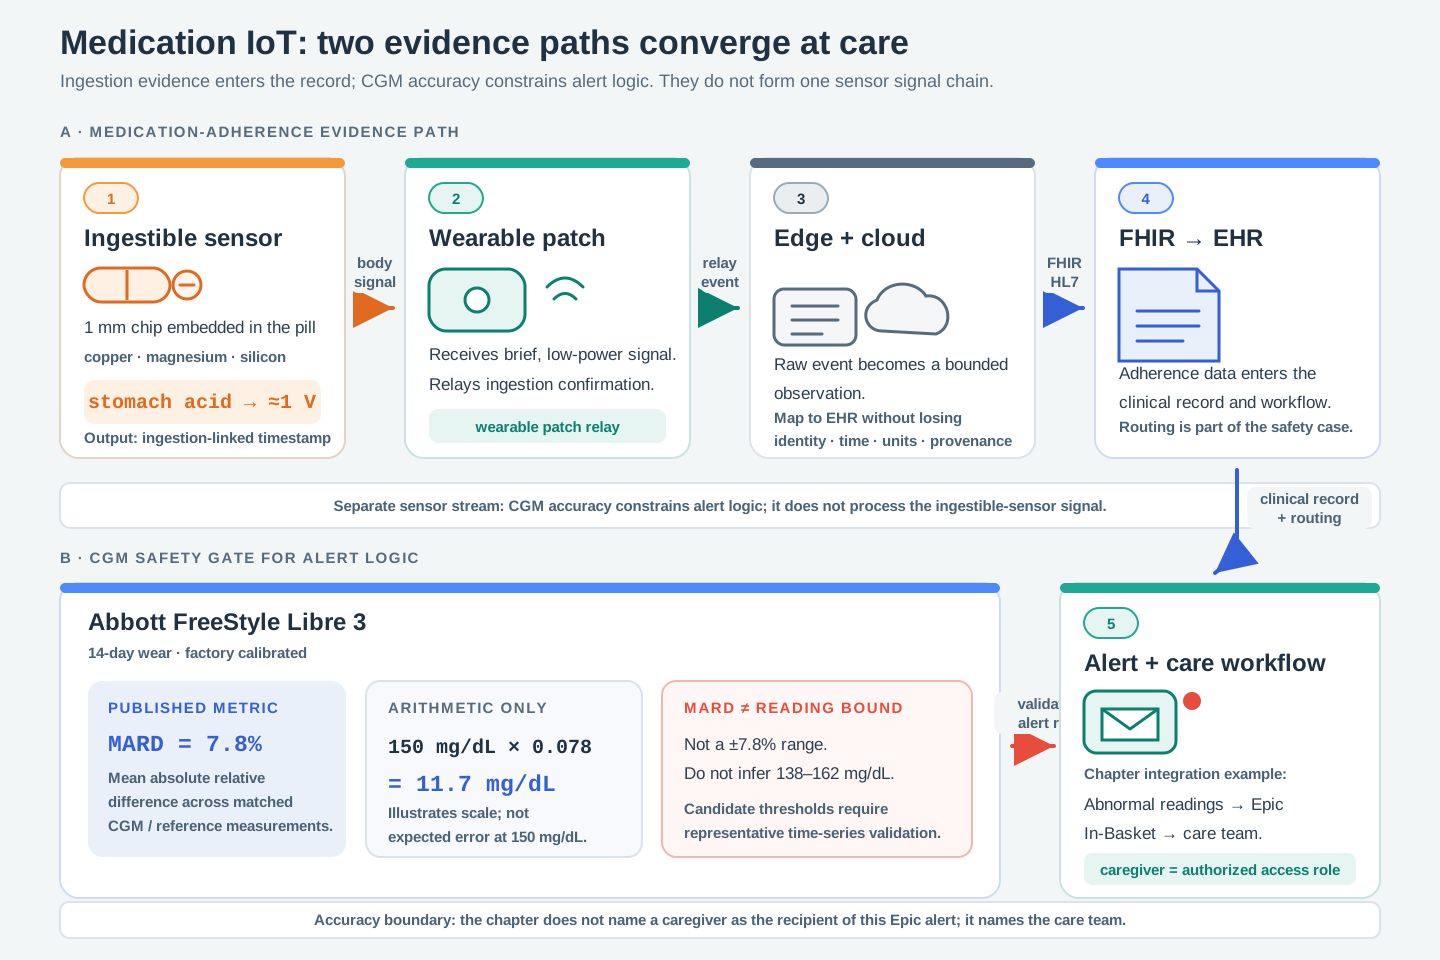
- The cloud platform must then map it into the EHR through FHIR or HL7 without losing patient identity, time, units, or provenance.
Major section
Heart Failure Readmission ROI
Result: Under these assumptions, gross avoided admission costs are about 2.45 times program cost and net modeled savings about 1.45 times cost; payer reimbursement is a separate uncertain line item.
- Any modeled benefit depends on validating avoided admissions and separately accounting for treatment costs, CMS payment adjustments, device purchase, connectivity, integration and staff.
- Key insight: Healthcare IoT economics depend on separately modeled treatment costs, payer adjustments, device and connectivity costs, integration, and staff; do not equate an avoided admission with an avoided CMS penalty.
- Scenario: A health system deploys smart pill bottles for heart failure patients to improve medication adherence and reduce hospital readmissions.
Major section
Medication IoT Relationships
HIPAA Compliance: PHI protection adds roughly $4 per patient per month in operating cost.
- CGM Accuracy (7.8% MARD): Aggregate accuracy must not be mistaken for a per-reading bound; alert logic needs device-specific evidence.
- Active vs Passive Monitoring: The design shift moves from patient-triggered tests to continuous background sensing.
- Missing any element causes deployment failure.
Deck summary
Key takeaways
The Integration Gap: Despite the promise of consumer health wearables and IoT medical devices, lack of Electronic Health Record (EHR) integration remains the primary barrier to clinical adoption.
- "Sometimes, a dumb gadget can be as useful as a smart one if it could integrate seamlessly with the EHR.".
- Result: Under these assumptions, gross avoided admission costs are about 2.45 times program cost and net modeled savings about 1.45 times cost; payer reimbursement is a separate uncertain line item.
- HIPAA Compliance: PHI protection adds roughly $4 per patient per month in operating cost.
Retrieval practice
Recall check

Ada says: answer from memory, then check your reasoning.
Q1A continuous glucose monitor (CGM) has a published MARD of 7.8%. What is the MOST appropriate way to use that figure when designing dosing decision support?
Show answer
Answer: C MARD describes average absolute relative difference under the study conditions.
Q2For the same medication, patient group, and validated basic sensing requirement, a care team uses Epic records to act on adherence events. Option A is a 15-sensor AI bottle with no EHR integration; option B is a simple weight-sensor bottle whose observations reach the team through reviewed FHIR mapping. Which approach is more likely to fit this clinical workflow?
Show answer
Answer: D Both options meet the stated basic sensing need, but B carries the observation into the team’s Epic workflow through reviewed FHIR mapping.
Q3An ingestible sensor system uses a 1mm chip made of copper, magnesium, and silicon that is embedded in a medication pill. When the pill dissolves in the stomach, stomach acid acts as an electrolyte to generate approximately 1 volt. The signal is transmitted through body tissue to a wearable patch. What is the PRIMARY advantage of this approach over a smart pill bottle with a lid-open sensor?
Show answer
Answer: B The bottle observes access to pills, while the ingestible chip can generate an event after contact with stomach fluid.
Q4A diabetes management app consumes readings from a CGM with a published MARD of 7.8%. Which design approach is safest?
Show answer
Answer: A This preserves the context needed to interpret a reading, traces confirmation prompts to approved labeling, and tests candidate alerts against actual performance distributions instead of deriving them from MARD.
Q5What compares dose evidence with the prescription, escalates unresolved gaps and records the outcome?
Show answer
Answer: B The care workflow compares evidence with the prescribed schedule, escalates an unresolved gap, and records a concise result for the patient, caregiver, or clinician.
Q6Complete the medication adherence escalation gate:
Show answer
Answer: A Medication adherence alerts should respect active orders, patient consent, event confidence, and care-plan escalation windows before notifying a caregiver.
Print reference
Answers 1 of 2
Answer key.
- C · MARD describes average absolute relative difference under the study conditions.
- D · Both options meet the stated basic sensing need, but B carries the observation into the team’s Epic workflow through reviewed FHIR mapping.
- B · The bottle observes access to pills, while the ingestible chip can generate an event after contact with stomach fluid.
Print reference
Answers 2 of 2
Answer key.
- A · This preserves the context needed to interpret a reading, traces confirmation prompts to approved labeling, and tests candidate alerts against actual performance distributions instead of deriving them from MARD.
- B · The care workflow compares evidence with the prescribed schedule, escalates an unresolved gap, and records a concise result for the patient, caregiver, or clinician.
- A · Medication adherence alerts should respect active orders, patient consent, event confidence, and care-plan escalation windows before notifying a caregiver.